📍 Briarwood · New York · Commack·📞 631-315-1400·Mon–Sat 9am–8pm · Sunday by appointment
Dr. Peter Kampf & Associates
  • About
  • Procedures
  • Dental Implants
  • Full-Arch
  • Wisdom Teeth
  • Sedation
  • Patient Info
  • Technology
  • Testimonials
  • Contact
  • Locations
AboutProceduresDental ImplantsFull-ArchWisdom TeethSedationPatient InfoTechnologyTestimonialsContactLocations📞 631-315-1400
← Back to Home/New Patient Registration & Health History

New patient forms

New Patient Registration & Health History

Registration, dental history and medical history in one packet.

Book a Consultation

Review, complete, and bring to your visit

This is the full 4-page form supplied by our practice. Complete your registration, dental history and medical history below. Include your current medicines and allergies; bring a separate list if you need more space. Leave office-use fields for our team. Initial only statements you understand and have discussed. Signatures should be completed after your questions have been answered; signature lines remain blank in this online preparation version.

Your entries are not submitted or stored by this form. Leaving or refreshing clears them. Print or save a copy on a device you trust, and bring it to your appointment. Do not send completed forms through the general contact form.

On a small screen, scroll sideways to see the complete page. For more convenient editing, download the fillable PDF and open it in a PDF reader.

Download Fillable PDF · 4 pagesBack to Patient Forms

Page 1 of 4

Read page 1 as text
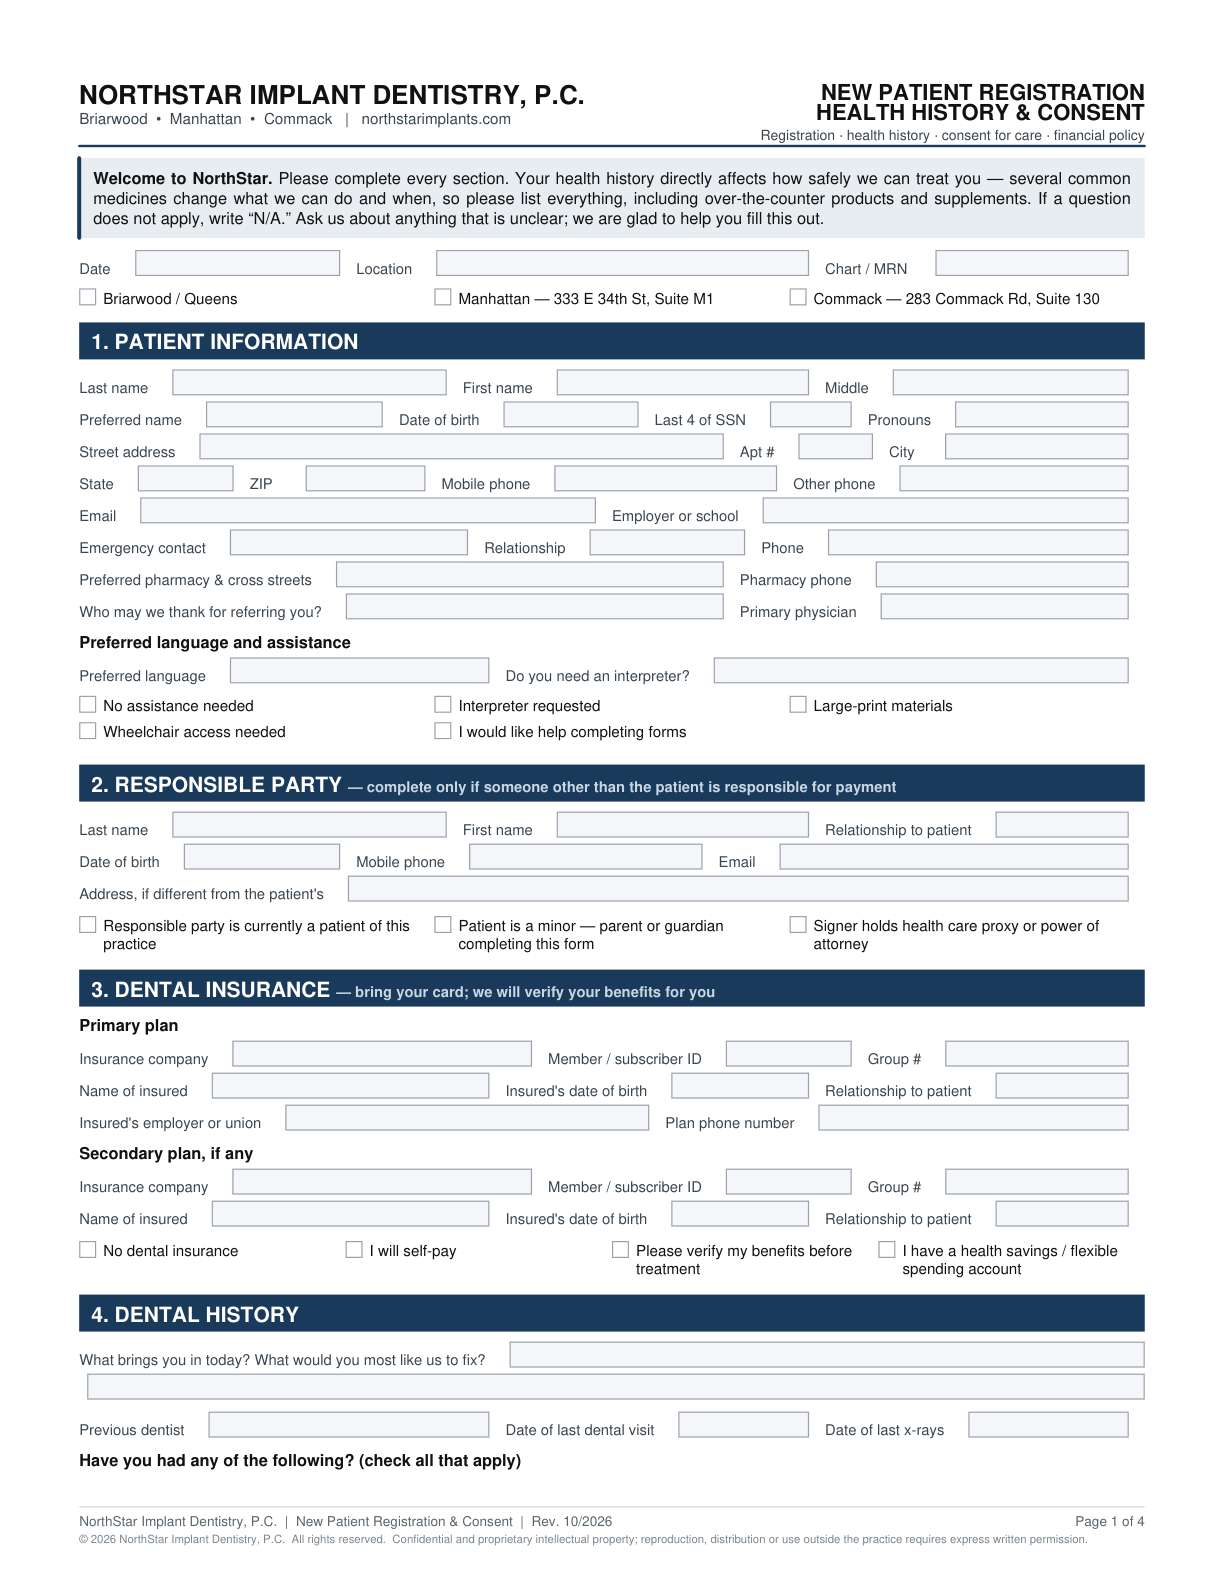
NorthStar Implant Dentistry, P.C. | New Patient Registration & Consent | Rev. 10/2026 Page 1 of 4 © 2026 NorthStar Implant Dentistry, P.C. All rights reserved. Confidential and proprietary intellectual property; reproduction, distribution or use outside the practice requires express written permission. NORTHSTAR IMPLANT DENTISTRY, P.C. Briarwood • Manhattan • Commack | northstarimplants.com NEW PATIENT REGISTRATION HEALTH HISTORY & CONSENT Registration · health history · consent for care · financial policy Welcome to NorthStar. Please complete every section. Your health history directly affects how safely we can treat you — several common medicines change what we can do and when, so please list everything, including over-the-counter products and supplements. If a question does not apply, write “N/A.” Ask us about anything that is unclear; we are glad to help you fill this out. Date Location Chart / MRN Briarwood / Queens Manhattan — 333 E 34th St, Suite M1 Commack — 283 Commack Rd, Suite 130 1. PATIENT INFORMATION Last name First name Middle Preferred name Date of birth Last 4 of SSN Pronouns Street address Apt # City State ZIP Mobile phone Other phone Email Employer or school Emergency contact Relationship Phone Preferred pharmacy & cross streets Pharmacy phone Who may we thank for referring you? Primary physician Preferred language and assistance Preferred language Do you need an interpreter? No assistance needed Interpreter requested Large-print materials Wheelchair access needed I would like help completing forms 2. RESPONSIBLE PARTY — complete only if someone other than the patient is responsible for payment Last name First name Relationship to patient Date of birth Mobile phone Email Address, if different from the patient's Responsible party is currently a patient of this practice Patient is a minor — parent or guardian completing this form Signer holds health care proxy or power of attorney 3. DENTAL INSURANCE — bring your card; we will verify your benefits for you Primary plan Insurance company Member / subscriber ID Group # Name of insured Insured's date of birth Relationship to patient Insured's employer or union Plan phone number Secondary plan, if any Insurance company Member / subscriber ID Group # Name of insured Insured's date of birth Relationship to patient No dental insurance I will self-pay Please verify my benefits before treatment I have a health savings / flexible spending account 4. DENTAL HISTORY What brings you in today? What would you most like us to fix? Previous dentist Date of last dental visit Date of last x-rays Have you had any of the following? (check all that apply)
Original form page 1; full text is available above

Page 2 of 4

Read page 2 as text
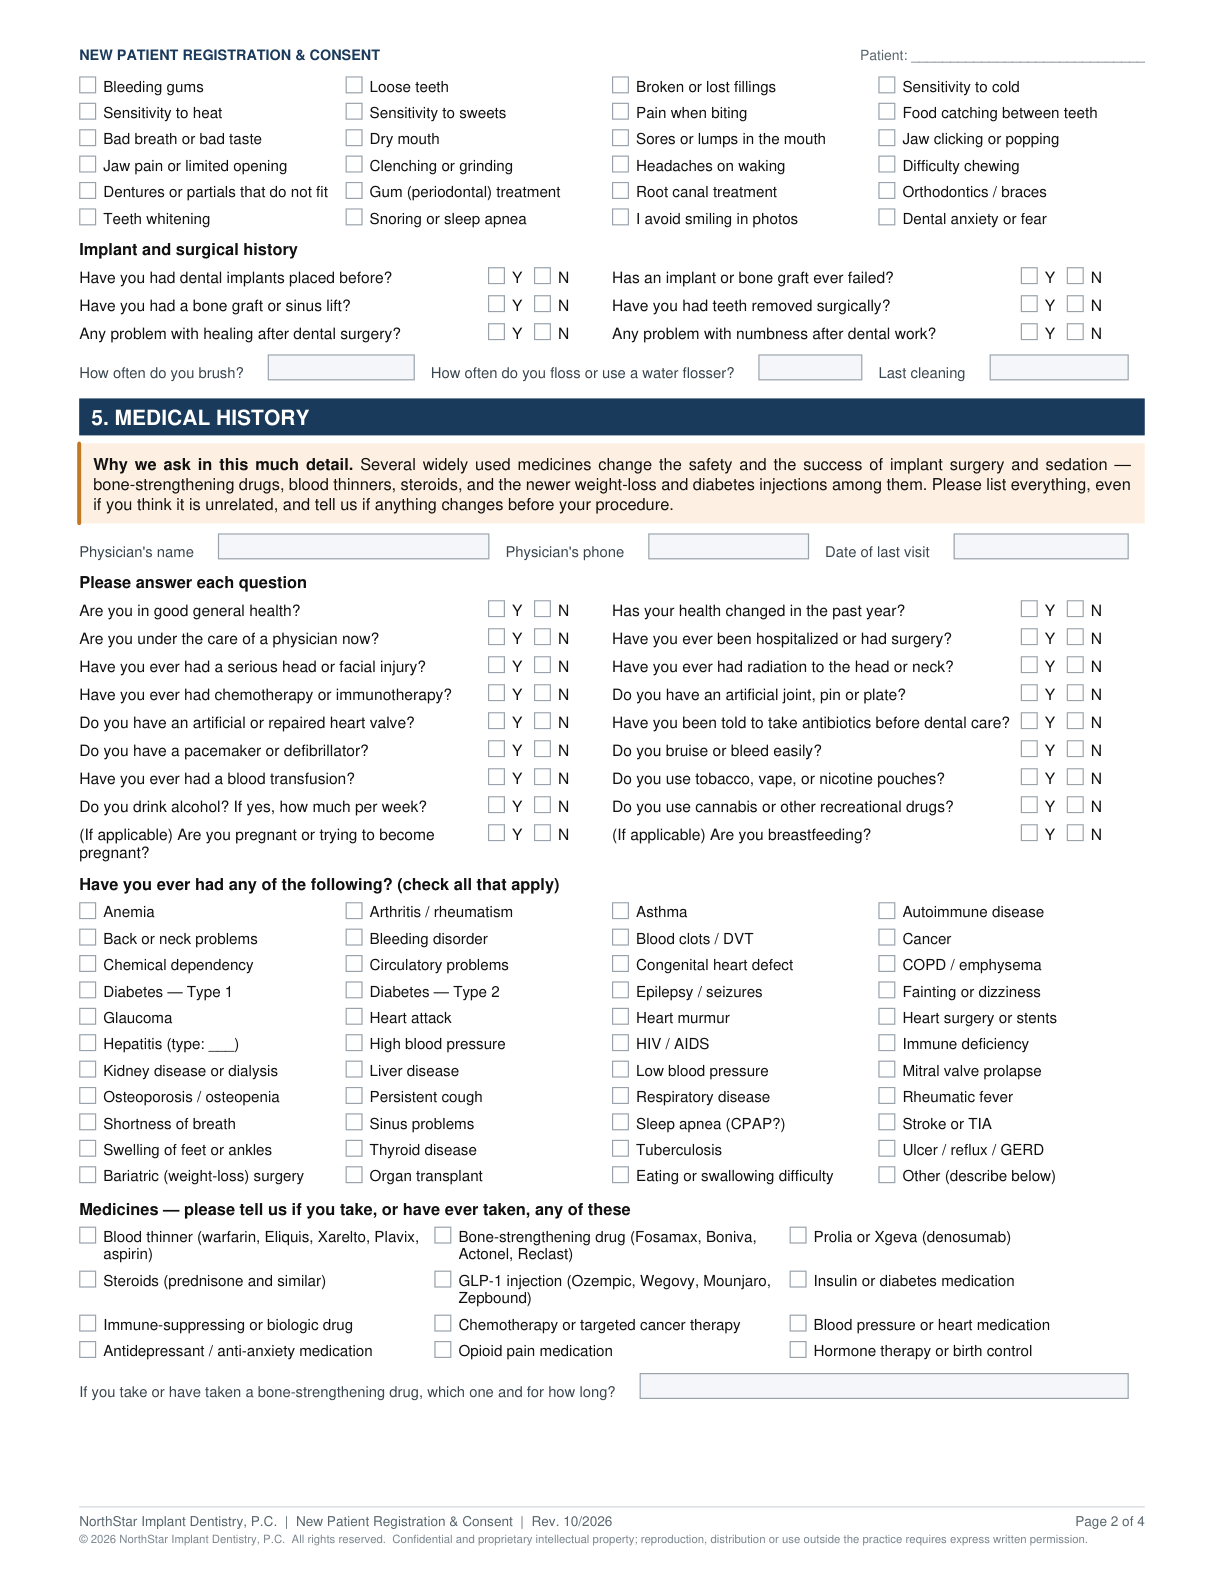
NorthStar Implant Dentistry, P.C. | New Patient Registration & Consent | Rev. 10/2026 Page 2 of 4 © 2026 NorthStar Implant Dentistry, P.C. All rights reserved. Confidential and proprietary intellectual property; reproduction, distribution or use outside the practice requires express written permission. NEW PATIENT REGISTRATION & CONSENT Patient: ______________________________ Bleeding gums Loose teeth Broken or lost fillings Sensitivity to cold Sensitivity to heat Sensitivity to sweets Pain when biting Food catching between teeth Bad breath or bad taste Dry mouth Sores or lumps in the mouth Jaw clicking or popping Jaw pain or limited opening Clenching or grinding Headaches on waking Difficulty chewing Dentures or partials that do not fit Gum (periodontal) treatment Root canal treatment Orthodontics / braces Teeth whitening Snoring or sleep apnea I avoid smiling in photos Dental anxiety or fear Implant and surgical history Have you had dental implants placed before? Y N Has an implant or bone graft ever failed? Y N Have you had a bone graft or sinus lift? Y N Have you had teeth removed surgically? Y N Any problem with healing after dental surgery? Y N Any problem with numbness after dental work? Y N How often do you brush? How often do you floss or use a water flosser? Last cleaning 5. MEDICAL HISTORY Why we ask in this much detail. Several widely used medicines change the safety and the success of implant surgery and sedation — bone-strengthening drugs, blood thinners, steroids, and the newer weight-loss and diabetes injections among them. Please list everything, even if you think it is unrelated, and tell us if anything changes before your procedure. Physician's name Physician's phone Date of last visit Please answer each question Are you in good general health? Y N Has your health changed in the past year? Y N Are you under the care of a physician now? Y N Have you ever been hospitalized or had surgery? Y N Have you ever had a serious head or facial injury? Y N Have you ever had radiation to the head or neck? Y N Have you ever had chemotherapy or immunotherapy? Y N Do you have an artificial joint, pin or plate? Y N Do you have an artificial or repaired heart valve? Y N Have you been told to take antibiotics before dental care? Y N Do you have a pacemaker or defibrillator? Y N Do you bruise or bleed easily? Y N Have you ever had a blood transfusion? Y N Do you use tobacco, vape, or nicotine pouches? Y N Do you drink alcohol? If yes, how much per week? Y N Do you use cannabis or other recreational drugs? Y N (If applicable) Are you pregnant or trying to become pregnant? Y N (If applicable) Are you breastfeeding? Y N Have you ever had any of the following? (check all that apply) Anemia Arthritis / rheumatism Asthma Autoimmune disease Back or neck problems Bleeding disorder Blood clots / DVT Cancer Chemical dependency Circulatory problems Congenital heart defect COPD / emphysema Diabetes — Type 1 Diabetes — Type 2 Epilepsy / seizures Fainting or dizziness Glaucoma Heart attack Heart murmur Heart surgery or stents Hepatitis (type: ___) High blood pressure HIV / AIDS Immune deficiency Kidney disease or dialysis Liver disease Low blood pressure Mitral valve prolapse Osteoporosis / osteopenia Persistent cough Respiratory disease Rheumatic fever Shortness of breath Sinus problems Sleep apnea (CPAP?) Stroke or TIA Swelling of feet or ankles Thyroid disease Tuberculosis Ulcer / reflux / GERD Bariatric (weight-loss) surgery Organ transplant Eating or swallowing difficulty Other (describe below) Medicines — please tell us if you take, or have ever taken, any of these Blood thinner (warfarin, Eliquis, Xarelto, Plavix, aspirin) Bone-strengthening drug (Fosamax, Boniva, Actonel, Reclast) Prolia or Xgeva (denosumab) Steroids (prednisone and similar) GLP-1 injection (Ozempic, Wegovy, Mounjaro, Zepbound) Insulin or diabetes medication Immune-suppressing or biologic drug Chemotherapy or targeted cancer therapy Blood pressure or heart medication Antidepressant / anti-anxiety medication Opioid pain medication Hormone therapy or birth control If you take or have taken a bone-strengthening drug, which one and for how long?
Original form page 2; full text is available above

Page 3 of 4

Read page 3 as text
NorthStar Implant Dentistry, P.C. | New Patient Registration & Consent | Rev. 10/2026 Page 3 of 4 © 2026 NorthStar Implant Dentistry, P.C. All rights reserved. Confidential and proprietary intellectual property; reproduction, distribution or use outside the practice requires express written permission. NEW PATIENT REGISTRATION & CONSENT Patient: ______________________________ List every medicine and supplement you take, with the reason for it (attach a list or a photo of your bottles if easier): Allergies and reactions — medicines, latex, metals, foods, anesthetics (describe what happens): Anything else we should know about your health, or anything you would like to tell us privately: 6. HOW WE MAY CONTACT YOU — you may change any of these at any time We use calls, texts and email for appointment reminders, test and biopsy results, treatment plans, and billing. Message and data rates may apply; you can reply STOP to any text to stop receiving them. You may contact me by: Text message to my mobile Phone call to my mobile Phone call to my other number Email Mail to my home address Patient portal only You may leave a detailed message: Yes, on my voicemail Yes, with the people listed below Appointment times only — no clinical details No messages — please keep trying People we may speak with about your care (name and relationship) 7. CONSENT FOR CARE AND USE OF MY INFORMATION • Consent to examination and routine care. I authorize NorthStar Implant Dentistry, P.C., its dentists, contractors and staff to examine me, take x-rays, photographs and scans, and provide dental care for this visit and for later visits. Surgery, sedation and other significant procedures are consented to separately, on their own forms, after a discussion of the risks, benefits and alternatives. I may revoke this consent in writing at any time. • My dental record. This practice is required by law to keep records of my care. Those records are used and disclosed only as permitted by state and federal privacy law, as described in the practice's Notice of Privacy Practices, which I may ask to see at any time and which may be updated from time to time. • Insurance. I authorize this practice to release the information necessary to process my claims, and I assign to the practice the dental benefits otherwise payable to me for the services provided. I authorize the use of this signature on my insurance submissions. This authorization ends when my current treatment plan is complete or one year from the date I sign, whichever comes first. • Accuracy. To the best of my knowledge the information I have given is complete and correct, and I will tell this office if my health, medicines or insurance change — including between the day I sign this and the day of any procedure. I received the Notice of Privacy Practices I declined a copy of the Notice Copy of this packet offered to me 8. FINANCIAL POLICY We would rather talk about money before treatment than after it. Please read this section and ask us anything. • Estimates before treatment. Before any treatment beyond an examination, you receive a written treatment plan with the fees, what we estimate your plan will cover, and your estimated share. An estimate is not a guarantee of what your plan will pay. • Your insurance is a contract between you and your plan. We are not a party to it. As a courtesy we verify your benefits and file your claims, and we will bill a secondary plan once the primary has paid. It is your responsibility to confirm that your treating doctor is in your plan's network. All charges are ultimately your responsibility, including anything your plan does not cover. • What is due when. Co-payments, deductibles and the estimated patient portion are due at the time of service. Surgical and implant treatment may require a deposit when it is scheduled. After your plan responds, we bill you for any remaining balance or refund any overpayment. • If you do not have insurance. Payment in full is due at the time of service unless we have approved a written payment arrangement in advance. We will tell you about any financing or membership options we offer. • Past-due balances. A balance unpaid 30 days after our statement may be charged a late fee of 1% per month (12% per year), which is below the New York civil usury limit. If an account must be placed with a collection agency or attorney, you agree to pay the reasonable costs and fees actually incurred, to the extent New York law permits them.
Original form page 3; full text is available above

Page 4 of 4

Read page 4 as text
NorthStar Implant Dentistry, P.C. | New Patient Registration & Consent | Rev. 10/2026 Page 4 of 4 © 2026 NorthStar Implant Dentistry, P.C. All rights reserved. Confidential and proprietary intellectual property; reproduction, distribution or use outside the practice requires express written permission. NEW PATIENT REGISTRATION & CONSENT Patient: ______________________________ • What we will not do. Consistent with New York's Fair Medical Debt Reporting Act, we do not report patient balances to consumer credit reporting agencies. If you are having trouble paying, call us — we would much rather arrange a plan than send an account out. • Returned payments. A service charge may be applied to any check or other payment returned unpaid. Appointments • Surgical and sedation appointments reserve a long block of time and a surgical team. Please give us at least two business days' notice to change or cancel one, and 24 hours for any other appointment. A fee may be charged for a late cancellation or a missed appointment, and a deposit may be required to reschedule. Late cancellation / missed appointment fee Deposit required for surgical scheduling 9. SIGNATURES Please initial each line: The health history I have given is complete and accurate, and I will report any change before my treatment. I consent to examination, x-rays and routine dental care as described in Section 7, and I understand that surgery and sedation require their own separate consent. I have read and agree to the financial policy in Section 8, including the appointment and cancellation policy. I have been offered a copy of this packet and of the Notice of Privacy Practices. Signature of patient or legal representative Date Time Print name If not the patient: relationship and legal authority (parent, guardian, health care proxy, power of attorney) Witness signature (optional) Print name Date OFFICE USE Photo ID and insurance card scanned Benefits verified Health history reviewed with patient Medical clearance needed Premedication indicated Blood thinner protocol flagged Bone-strengthening drug flagged (MRONJ) Packet scanned to chart Reviewed by Date / time Next update due Staff notes / items to follow up before treatment: Retention: scan this packet into the patient record at the first visit. Health history is re-confirmed at every surgical visit and re-taken at least once a year, or sooner if the patient reports a change.
Original form page 4; full text is available above

NorthStar Implant Dentistry  ·  Briarwood · New York · Commack  ·  631-315-1400

© 2026 NorthStar Implant Dentistry, P.C. All rights reserved. NorthStar Implant Dentistry™, the NorthStar compass wheel design, and “Guiding Patients One Smile at a Time”™ are trademarks of NorthStar Implant Dentistry, P.C.

← Return to Homepage·Terms of Use